
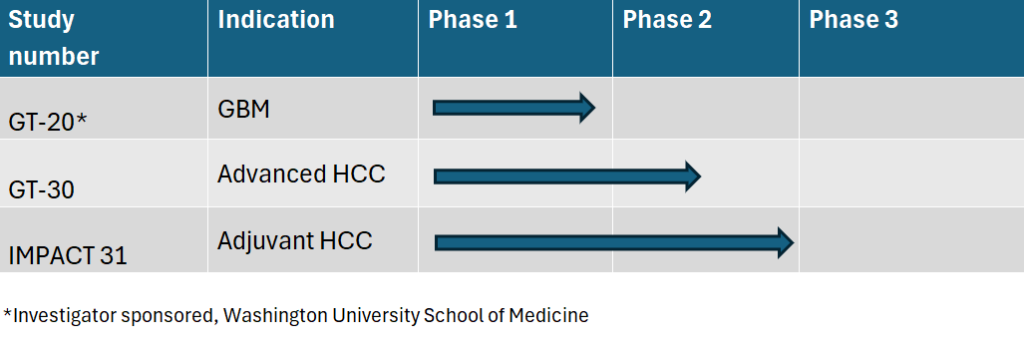
Geneos is currently pursuing clinical development to treat cancer patients with personalized neoantigen-directed immunotherapy.
1
Hepatocellular Carcinoma (Geneos-sponsored Studies)
- GT-30: Phase 1b/2a single-arm clinical trial of GNOs-PV02 + pembrolizumab to treat patients with advanced hepatocellular carcinoma (HCC). Click here for more information about the clinical trial.
- GT-31: Phase 2b, open-label, randomized, controlled clinical trial of GNOS-PV02 vs. active surveillance as adjuvant immunotherapy in patients with HCC. Click here for more information about the clinical trial.
2
GBM/Anaplastic Astrocytoma
- GT-20: an investigator-sponsored Phase I clinical trial in collaboration with Washington University School of Medicine to treat patients with newly diagnosed glioblastoma multiforme (GBM). Click here for more information about the clinical trial.
About GBM
Glioblastoma (GBM) is the most prevalent and aggressive primary malignant brain tumor in adults, accounting for about 52% of all primary brain malignancies. The estimated incident of GBM is 3.28 cases per 100,000 individuals, with a median age at diagnosis of 66 years. Despite aggressive treatment strategies, which typically involve surgical resection, radiotherapy and adjuvant temozolomide, median overall survival is dismal – only 12-18 months. Within the context of GBM, patients with an unmethylated O6-methylguanine-DNA methyltransferase form of GBM (unmethylated GBM) have a poorer prognosis. In addition, GBM is associated with high recurrence rates, largely due to tumor heterogeneity and inherent resistance mechanisms.
To date, immunotherapies for GBM have largely failed to elicit meaningful clinical outcomes. Factors contributing to the suboptimal therapeutic responses include: 1) a profoundly immunosuppressive tumor microenvironment, 2) the presence of glioblastoma stem cells that evade immune recognition, and 3) adaptive resistance mechanisms that undermines the benefit of immune checkpoint inhibitors. Therefore, new therapeutic options are urgently needed.
On GT-20, Geneos is testing GNOS-PV01 (our personalized neoantigen-targeted immunotherapy delivered intramuscularly) in combination with IL-12 adjuvant for the treatment of patients with newly diagnosed unmethylated GBM following surgery and radiation.
About HCC
Primary liver cancer is the third leading cause of cancer-related deaths worldwide and the sixth most diagnosed cancer overall. Hepatocellular carcinoma (HCC) is the most common type of primary liver cancer, accounting for up to 80% of all cases. HCC is a significant global health challenge due to its high mortality rate ¾ the 5-year survival rate is approximately 18%.
The prevalence of HCC rises with age and is caused by a confluence of somatic mutations, immune system inactivation, and extended exposure to risk factors. HCC is closely linked to chronic infections such as hepatitis B and hepatitis C virus, alcohol‐associated liver disease (ALD), and metabolic dysfunction‐associated steatotic liver disease (MASLD). While the adoption of vaccination programs and antiviral therapies have reduced the incidence of viral-induced HCC, the incidence of MASLD‐related HCC is increasing. In turn, the global burden of HCC has increased over time, highlighting the need for effective systemic therapies to improve patient outcomes.
Most patients with HCC present at an advanced stage and are not suitable for curative treatments. Over the past 5 years, immunotherapy combinations have superseded tyrosine kinase inhibitor therapy as the standard first-line therapy for patients with advanced HCC. These therapies include the combination of a checkpoint inhibitors (anti-programmed cell death 1 [PD1]/anti-programmed death ligand 1 [PDL1]) with an anti-cytotoxic T-lymphocyte associated protein 4 [CTLA-4] or partner with anti-vascular endothelial growth factor [VEGF]. Unfortunately, only about 20%-30% of patients respond to first-line immunotherapy combinations, and about 50% of these individuals develop disease progression at 6 months.
About Geneos Clinical Trials in HCC
The GT-30 trial was a single-arm, open-label, phase 1/2 study of a DNA plasmid vaccine (GNOS-PV02) encoding up to 40 neoantigens coadministered with plasmid-encoded interleukin-12 (IL-12) plus pembrolizumab (anti-PD1) in patients with advanced HCC previously treated with a multityrosine kinase inhibitor. Results from the study demonstrated that the combination of GNOS-PV02 plus pembrolizumab was safe and showed an objective response rate of 30.6% among the 36 patients studied.*
While most patients with HCC have advanced disease at diagnosis, some patients have their cancer detected early and may benefit from surgical resection to remove the cancer. However, despite surgery with intent to cure, most of these patients are at high risk for disease recurrence – their disease typically returns within 2 years. Currently, there are no approved therapies for HCC in the adjuvant setting (post-surgery).
The GT-31 trial is a randomized Phase 2 clinical trial in patients with high-risk HCC who have undergone surgical resection with curative intent. The trial evaluates the efficacy of GNOS-PV02 coadministered with plasmid-encoded IL-12 compared to the current standard of care (active surveillance) in high-risk patients following surgery.
* Yarchoan, M., Gane, E.J., Marron, T.U. et al. Personalized neoantigen vaccine and pembrolizumab in advanced hepatocellular carcinoma: a phase 1/2 trial. Nat Med 30, 1044–1053 (2024).